Note: This article discusses coronary artery stents used to improve blood flow to the heart. It is for general education, not a substitute for advice from your cardiologist. New, severe, or worsening chest pain, shortness of breath, cold sweats, fainting, or symptoms that feel like a heart attack require emergency care.
A coronary stent can sound like a tiny household part: install it, inspect it, replace it when it gets old. Fortunately, your heart is not a toaster, and a stent is not a filter that needs a scheduled swap every few years.
For most people, the answer is simple: coronary stents do not need routine replacement. A typical metal or drug-eluting stent is designed to remain in the artery permanently. However, the artery can sometimes narrow again inside or around the stent. This is called in-stent restenosis, and it may require another procedurenot because the original stent has “expired,” but because the blood vessel has changed.
Restenosis is not inevitable, and modern drug-eluting stents have greatly reduced the likelihood compared with older stent technology. Still, a stent treats one narrowed area; it does not erase the underlying coronary artery disease that caused the problem in the first place. Think of it as fixing one pothole on a road that still needs regular maintenance.
Do Coronary Stents Need to Be Replaced?
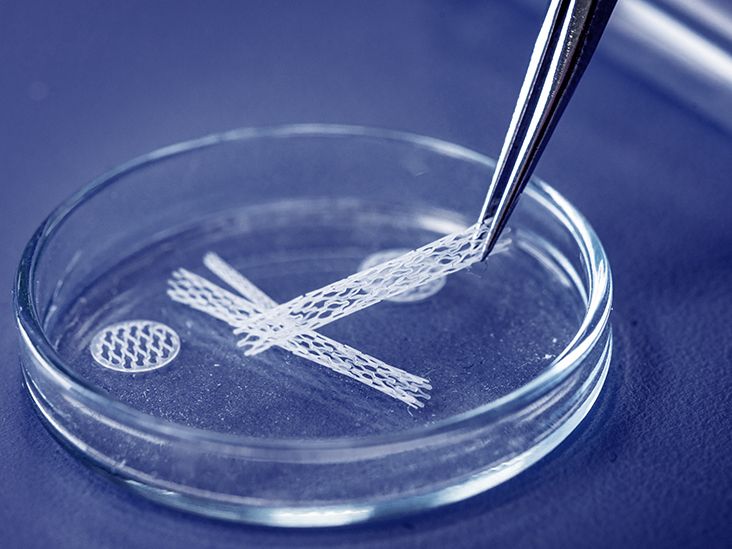
In most cases, no. Traditional coronary stents are small mesh tubes placed during angioplasty, also called percutaneous coronary intervention or PCI. A cardiologist guides a catheter through a blood vessel, inflates a balloon at the narrowed area, and expands the stent so it can support the artery wall and improve blood flow.
Once implanted, the stent becomes part of the artery’s landscape. The body gradually grows a lining over it, helping the vessel heal. The stent itself generally stays where it is for life, and cardiologists do not remove or replace it simply because several years have passed.
There are exceptions to the broad “stents are permanent” rule. Some specialized stents in other parts of the body, such as ureteral, airway, or certain vascular stents, may require monitoring, removal, or replacement. There are also biodegradable coronary stent technologies designed to dissolve over time. But when people ask whether a typical heart stent needs changing, they are usually talking about a metal or drug-eluting coronary stent that is intended to remain in place.
The important question is not usually, “When will my stent need to be replaced?” A more useful question is, “How do we know whether blood is still flowing well through the treated artery and the rest of my coronary circulation?”
What Is Restenosis?
Restenosis means a blood vessel has narrowed again after treatment. In-stent restenosis, often shortened to ISR, means that narrowing develops in the portion of the coronary artery that was previously treated with a stent.
After a stent is placed, the artery needs to heal. Normally, a thin layer of healthy tissue grows over the stent. In some cases, however, too much tissue grows within the stent, making the artery’s inner channel narrower again. This tissue response is sometimes described as scar tissue buildup or excessive healing. The artery is not being dramatic on purpose; it is simply healing with a little too much enthusiasm.
Restenosis can also be influenced by mechanical issues. For example, a stent may not have expanded fully during the original procedure, the artery may be heavily calcified, or plaque may continue to develop at the edges of the stent. Cardiologists can use detailed imaging from inside the artery, such as intravascular ultrasound or optical coherence tomography, to understand why restenosis happened and choose the best treatment.
Why Drug-Eluting Stents Matter
Most modern coronary stents are drug-eluting stents. These stents slowly release medication that helps limit excessive tissue growth in the artery. They are different from older bare-metal stents, which provide structural support but do not release medicine.
Drug-eluting stents have lowered the chance of restenosis, but “lower” does not mean “zero.” A patient can still develop narrowing years later, especially if the artery has complex disease or if major cardiovascular risks such as smoking, uncontrolled diabetes, high blood pressure, or high cholesterol remain untreated.
Restenosis vs. Stent Thrombosis: Why the Difference Matters
Restenosis and stent thrombosis are both serious stent-related problems, but they are not the same thing.
Restenosis is usually a gradual re-narrowing caused by tissue growth, plaque progression, or mechanical factors. It may cause recurring chest pressure during exertion, reduced exercise tolerance, fatigue, or shortness of breath. Sometimes it causes no obvious symptoms at all.
Stent thrombosis is a blood clot that forms in or near the stent and abruptly blocks blood flow. This can trigger a heart attack and is an emergency. Antiplatelet medication is commonly prescribed after stent placement to reduce the risk of clot formation. Stopping medicines such as clopidogrel without speaking with the prescribing clinician can increase the risk of dangerous clotting, particularly soon after a stent procedure.
In plain English: restenosis is often more like a lane slowly getting narrower, while stent thrombosis can be like a sudden roadblock. Both deserve medical attention, but sudden symptoms require urgent action.
Who Is More Likely to Develop In-Stent Restenosis?
Anyone with a coronary stent can develop restenosis, but some factors can raise the odds. These include diabetes that is not well controlled, smoking, kidney disease, high cholesterol, high blood pressure, and complex or extensive coronary artery disease. Smaller arteries and heavily calcified arteries can also be more technically challenging to treat.
There is an important distinction here: restenosis is not always caused by a person doing something “wrong.” Sometimes it is related to the biology of healing, the anatomy of the artery, or the complexity of the original blockage. Still, lifestyle choices and long-term risk-factor control can make a meaningful difference in protecting the stented artery and the rest of the heart’s circulation.
Symptoms of Restenosis After a Stent
Some people with in-stent restenosis have no symptoms. Others notice a return of the same problems they experienced before their original angioplasty. A person may feel chest pressure while walking uphill, get winded more easily, feel unusually tired, or develop discomfort that spreads to the shoulder, arm, jaw, neck, or back.
Possible symptoms include:
- Chest pain, pressure, squeezing, or heaviness
- Shortness of breath during activity or at rest
- Unusual fatigue or reduced exercise tolerance
- Lightheadedness, nausea, sweating, or palpitations
- Pain in the arm, shoulder, jaw, neck, or upper back
Symptoms can be subtle, especially in older adults, women, and people with diabetes. Do not assume that new fatigue or breathlessness is “just getting older” or “just being out of shape.” It may be nothing urgent, but it deserves a conversation with a health professional.
If chest pain is severe, new, persistent, occurs at rest, or comes with sweating, fainting, nausea, or shortness of breath, call emergency services immediately. Do not drive yourself to the hospital or attempt to negotiate with your heart like it is a stubborn coworker.
How Doctors Check for Restenosis
There is no universal calendar that says every stent must be tested on a particular anniversary. Follow-up testing depends on symptoms, the reason for the original stent, the patient’s overall health, and the cardiologist’s clinical judgment.
If restenosis is suspected, a care team may use one or more of the following:
- Exercise stress testing: Evaluates whether exertion brings on signs of reduced blood flow to the heart.
- Coronary CT angiography: Produces detailed images of the heart arteries in selected patients.
- Cardiac catheterization and coronary angiography: Provides a direct view of the coronary arteries and can allow treatment during the same procedure.
- Fractional flow reserve: Measures the effect of a narrowing on blood flow.
- Intravascular ultrasound or optical coherence tomography: Gives detailed images from inside the artery and can help identify underexpansion, scar tissue, or plaque-related causes.
Coronary CT angiography can create three-dimensional images of coronary arteries, while invasive catheterization remains an important tool when doctors need a precise view of a suspected blockage or expect that treatment may be needed.
How Is In-Stent Restenosis Treated?
Treatment is personalized. The best option depends on how severe the narrowing is, where it is located, how many stent layers are already present, whether the artery is calcified, and whether there are other blockages elsewhere in the heart.
Repeat Balloon Angioplasty
A cardiologist may use a balloon catheter to reopen the narrowed area. In some cases, special balloons are used to modify scar tissue or improve expansion of an underexpanded stent. This may be appropriate when the restenosis is limited and the anatomy is favorable.
Another Drug-Eluting Stent
For certain patterns of restenosis, placing another drug-eluting stent may be recommended. The new stent can provide additional support and release medication that helps limit renewed tissue growth. However, placing multiple layers of metal inside a small artery is not always ideal, so cardiologists carefully weigh the benefits and long-term trade-offs.
Drug-Coated Balloon Treatment
A drug-coated balloon delivers medication to the artery wall without leaving another permanent metal scaffold behind. This can be especially useful when avoiding another stent layer is desirable. Professional cardiology guidance recognizes drug-coated balloons as an evidence-supported option for many cases of in-stent restenosis, although treatment selection still depends on the patient and the anatomy.
Intravascular Brachytherapy
For recurrent or complex restenosis, especially when several stent layers are already present, some specialized centers may use intravascular brachytherapy. This treatment delivers a controlled dose of radiation inside the artery to reduce excessive tissue growth. It is not needed for most people, but it can be an important option in difficult repeat cases.
Coronary Artery Bypass Surgery
Sometimes the best solution is not another catheter procedure. Coronary artery bypass grafting, or CABG, creates a new route for blood to flow around a blockage. It may be considered when restenosis is extensive, when several vessels have significant disease, or when the patient’s anatomy makes repeat stenting less suitable.
Can You Prevent Restenosis?
No strategy can guarantee that restenosis will never happen, but several steps can lower cardiovascular risk and help protect both the stent and the arteries around it.
- Take antiplatelet medicines, cholesterol medicines, blood pressure medicines, and diabetes medicines exactly as prescribed.
- Do not stop an antiplatelet drug without talking to the clinician who manages your stent.
- Quit smoking and avoid secondhand smoke.
- Keep blood pressure, cholesterol, and blood sugar under control.
- Choose a heart-healthy eating pattern that emphasizes fiber-rich foods and limits excess sodium, saturated fat, and trans fat.
- Stay physically active within the limits set by your health care team.
- Attend follow-up visits and cardiac rehabilitation if it is recommended.
A stent can improve blood flow, but it cannot cure coronary artery disease. That is why long-term care matters. Healthy habits, medication adherence, and regular medical follow-up work together like a heart-protection teamless glamorous than a superhero movie, but far more useful.
Questions to Ask Your Cardiologist After Stent Placement
Having a short list of questions can make follow-up visits more useful. Consider asking:
- What type of stent do I have, and where is it located?
- How long should I take each antiplatelet medication?
- Which symptoms should prompt me to call the office, and which require emergency care?
- Do I need cardiac rehabilitation?
- What exercise level is appropriate for me now?
- What are my targets for LDL cholesterol, blood pressure, and blood sugar?
- Do I need future stress testing or imaging based on my particular condition?
It is also wise to keep an updated medication list and tell every health professionalincluding dentists and surgeonsthat you have a coronary stent. Some procedures and medications may need planning around antiplatelet therapy.
Experiences After a Stent: What People Commonly Notice
Life after a stent can be surprisingly emotional. Even when the procedure goes smoothly, many people are left with a new awareness of every chest sensation, skipped heartbeat, deep breath, and staircase. A stent may be tiny, but the thoughts it inspires can take up an entire room.
Experience One: “I Felt Better, Then I Started Worrying About Every Twinge”
Consider a person who had chest pressure while walking the dog, received a coronary stent, and felt dramatically better within days. Suddenly, errands were easier and climbing stairs did not require a strategic pause halfway up. Then, a few weeks later, a harmless muscle ache after gardening felt frightening. Was the stent failing? Was it restenosis? Was it a heart attack?
This type of anxiety is common after a heart procedure. Not every chest sensation is cardiac, but new or concerning symptoms should never be ignored. The most helpful approach is often learning the specific warning signs from the care team, understanding when to call emergency services, and gradually returning to normal activity through a medically appropriate plan. Cardiac rehabilitation can also provide structure, monitored exercise, and reassurance for people who feel nervous about moving their bodies again.
Experience Two: “I Thought the Procedure Fixed Everything”
Another common experience is the realization that a stent is a powerful treatment but not a permanent permission slip to ignore heart health. Someone may feel so much better after PCI that medication routines begin to seem optional. A cholesterol pill gets skipped. Blood pressure checks become less frequent. Smoking becomes “only on weekends.” Follow-up appointments are delayed because life gets busy, which is what life does best.
Then a cardiology visit becomes a reset button. The person learns that the stent opened one narrowed segment, but coronary artery disease can continue in other places. The goal is not perfection. The goal is consistency: taking medicines, monitoring diabetes or blood pressure, staying active, eating in a heart-supportive way, and keeping follow-up appointments. Small, repeatable choices are usually more powerful than a dramatic two-week burst of kale and panic.
Experience Three: “My Symptoms Were Not Exactly Like Before”
Restenosis, new coronary narrowing, and other heart problems do not always arrive with movie-style chest clutching. A person may notice that they are unusually exhausted after a short walk, feel winded carrying groceries, or develop vague pressure in the chest rather than sharp pain. Someone else may have nausea, sweating, jaw discomfort, or a strange feeling that “something is off.”
For people with diabetes, symptoms can be especially subtle. For women, heart symptoms may also be less stereotypical than the classic image many people expect. The practical lesson is simple: compare your current ability with your usual ability. If an activity that was comfortable last month now causes breathlessness, pressure, fatigue, or discomfort, bring it up promptly with a clinician.
Experience Four: “The Medication Part Was Harder Than I Expected”
After a stent, patients may take several medicines: antiplatelet drugs, cholesterol-lowering medications, blood pressure treatments, diabetes medicines, or anti-angina drugs. Managing them can feel like running a small pharmacy from the kitchen counter. Cost, side effects, confusing instructions, travel, and simple forgetfulness can make adherence challenging.
The safest response is not to quietly stop a medication. Instead, contact the prescribing office or pharmacist. There may be a lower-cost option, a different schedule, or another medication that works better. Antiplatelet drugs deserve special attention because stopping them too soon can raise the risk of a clot forming in the stent.
Experience Five: “I Eventually Stopped Thinking About the Stent Every Day”
For many people, the long-term experience becomes less dramatic. The stent fades from daily thought and becomes part of medical history, like a scar or an old address. They take their medicines, stay active, attend checkups, and know which symptoms warrant attention. That is often the best outcome: not forgetting heart health, but no longer living in fear of every heartbeat.
A coronary stent is not a disposable part. It is a durable treatment that can restore blood flow and relieve symptoms, while long-term prevention helps protect the rest of the cardiovascular system.
Conclusion
Most coronary stents do not need routine replacement because they are designed to stay in the artery permanently. However, restenosis can occur when the treated artery narrows again due to tissue growth, plaque progression, or mechanical issues. Symptoms may resemble the original heart symptoms, including chest pressure, shortness of breath, fatigue, or reduced exercise tolerance.
The good news is that restenosis can often be evaluated and treated with repeat angioplasty, a drug-coated balloon, another drug-eluting stent, brachytherapy, or bypass surgery when needed. The strongest long-term strategy is ongoing partnership with a cardiology team, medication adherence, smoking cessation, healthy lifestyle habits, and prompt attention to new symptoms.